
Time Perception in Obsessive-Compulsive Disorder

Post by Anastasia Sares

The takeaway

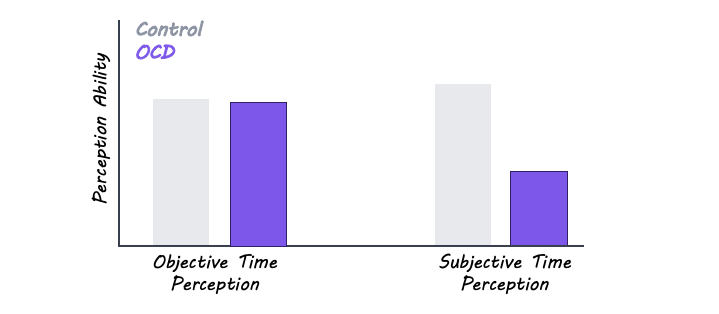
In a preliminary study designed to understand how people with obsessive-compulsive disorder may differ in time processing, the authors found that while objective time perception and movement ability were intact, subjective time perception (including time management, time knowledge, and time experience) was significantly impacted.

What's the science?

Obsessive Compulsive Disorder (OCD) is a condition in which a person experiences recurring worries (obsessions) and enacts certain behaviors (compulsions) to try and manage these worries. OCD shares some features with depression (for example, some depression medications that act on serotonin can also be used to treat OCD). It additionally shares features with movement disorders such as Tourette’s, where differences in brain function cause involuntary actions that are difficult for the person to control. 

People with OCD can take longer to complete certain tasks and experience difficulties with time management. However, it is currently unclear what contributes to this. One possibility is that people with OCD have more difficulty controlling their movements, which means that doing things takes more time. Another possibility is that their objective time perception is altered—they might be less able to estimate time passing due to differences in time-keeping mechanisms in the brain. Finally, a third possibility is that people with OCD differ in their subjective experience of time, which could include difficulty making plans or realizing how much time they have spent on a task.

Recently, in an exploratory study published in European Archives of Psychiatry and Clinical Neuroscience, Mavrogiorgou and colleagues tested both objective and subjective time perception, along with movement ability and depression/anxiety symptoms, to better understand whether OCD uniquely contributes to altered time processing.

How did they do it?

In this exploratory study, the authors recruited 20 participants with OCD and 20 healthy participants of similar ages and genders. They ran them through a battery of tests, including questionnaires to establish the severity of OCD symptoms, questionnaires for depression and anxiety symptoms, measures of movement ability, experimental tests to measure more concrete/objective aspects of time perception, and questionnaires about subjective aspects of time perception.

The objective time perception tasks included flicker fusion frequency, which presents a blinking light that flickers at faster and faster frequency until the participant indicates that they perceive it to be stable and not flickering anymore—this measures the timing resolution of their visual perception. Another was the Chronotest, where participants are presented with a light stimulus and asked to estimate how long it was on, in seconds. They are also asked to reproduce different time intervals by turning a light on for that amount of time.

What did they find?

Participants with OCD were not significantly different from the healthy controls in their objective time perception, and there was only a slight trend for a difference in movement ability. In contrast, subjective time measures such as time knowledge, time experience, and time management were significantly impaired in OCD, and were correlated with OCD symptoms—in other words, those with more severe OCD had poorer subjective time perception. Subjective time perception was also correlated with depression scores, both in people with OCD and in the healthy control group, but some influence of OCD symptoms remained even after controlling for depression, anxiety, and movement issues, specifically on time management. It’s worth noting that subjective time perception was measured using a questionnaire, while the objective time measures were done using experiments, so self-perception had more of a chance to influence the results.
What's the impact?

Since this is an exploratory study, it should be treated as preliminary, but it has the potential to increase our knowledge of a lesser-known aspect of OCD. If these results hold, it means that there are time perception differences in OCD that are not related to movement difficulties or depression/anxiety symptoms.
Access the original scientific publication here. 

Using Large Language Models to Map Grammar in the Brain

Post by Anastasia Sares

The takeaway

This study shows that grammatical features are encoded by individual neurons in the brain, distinct from other characteristics of the speech signal. Grammar-sensitive neurons are distributed throughout the left hemisphere in a way that is hard to detect when averaging regional activity.

What's the science?

Since the time of Broca, scientists have developed more and more detailed maps of the language-processing areas of the human brain. They have used a variety of brain imaging techniques, including functional magnetic resonance imaging (fMRI), electroencephalography (EEG), and others. All of these techniques have been helpful, but still lack the precise detail of single-neuron recording that is done routinely in animals. The only time that electrodes are implanted in human brains is when they are already undergoing an operation, such as for epilepsy. During those times when the brain is exposed, researchers can gather precious single-neuron data.

One challenge about studying human language processing is the complexity of language itself. In everyday conversation, we are free to put together words in a myriad of forms and sentence structures. Most of the time, studies of language involve presenting pre-designed words, phrases, or sentences that have a feature we are interested in (for example, sentences with different relationships between the subject and the object). However, this eliminates the natural spontaneity of language production, and so we can’t be sure if the brain activity we observe is reflecting what our brains do daily.

Fortunately, the technology behind large language models (some of which are now commonly referred to as “AI,” though not all of them are on the same scale) has given us the ability to represent natural language production in a way that computers can digest, and we can identify interesting features without having to design awkward stimuli. This week in Nature, Cai and colleagues combined natural language processing and recordings from electrodes implanted in the brains of epilepsy patients to map human language production, including grammatical features.

How did they do it?

The authors had access to eight people who were undergoing surgery for epilepsy. At the time of their operations, the patients consented to have an array of electrodes temporarily implanted in their brains so that the researchers could gather data about the firing of individual neurons. Depending on the patient, these electrode arrays were located in different spots in the brain, so the researchers had a variety of brain regions represented.

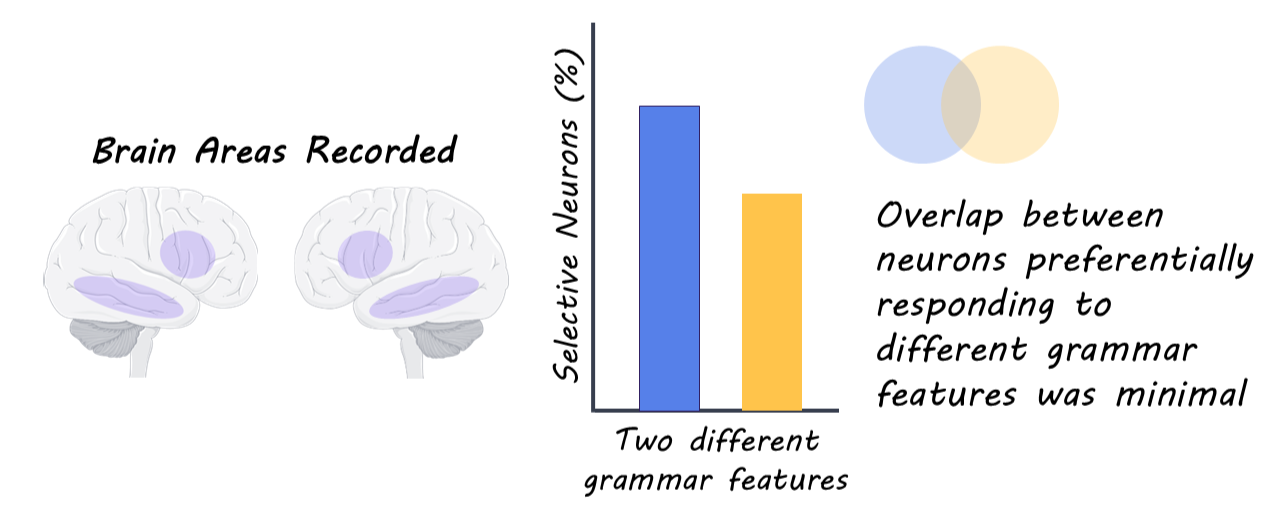
After implantation, the researchers recorded brain activity through the electrodes while asking the participant questions and allowing them to respond freely. They recorded these conversations and applied natural language processing algorithms to classify each sample of speech. In addition to representing the individual words, this approach extracts both grammatical relationships and the hierarchical structure of phrases (see image below). By labeling these features, the authors could then look at which parts of the brain were selectively responding to parts of speech, hierarchical features, or specific conversation contexts.

What did they find?

About 9% of neurons responded specifically to a word’s part of speech (noun, adjective, verb, etc). About 16% of neurons responded to constituency depth (how deep the word was in the nested hierarchy of the sentence), and so on. These neurons had very little overlap with each other, or with neurons that tracked other features of the speech (like the meaning of the word itself, or whether the pitch of the spoken word was high or low). Interestingly, these neurons that responded to different grammatical features were scattered throughout various brain regions, which may explain why it has been hard to pinpoint grammatical processing in the brain by summing up large amounts of activity. In addition, these grammar-selective neurons appeared in both hemispheres of the brain, but the most strongly predictive ones were in the left hemisphere, which lines up with decades of research confirming that language is processed on the left side of the brain (for most people).

What's the impact?

The results of this study inform debates about how the brain processes language. First, it supports the idea that certain high-level features of language can be coded by single neurons, rather than being only a result of multiple neurons firing in a pattern. These results also suggest that the popular but simplistic “modular” approach, where “region X is responsible for function Y,” doesn’t really work here: grammar-sensitive neurons are scattered throughout the left hemisphere.

Access the original scientific publication here. 

How Word Processing and Facial Recognition Adapt After Stroke

Post by Amanda Engstrom

The takeaway

Within the brain, facial recognition is lateralized to the right, and word processing is lateralized to the left. In individuals who suffer an early stroke in the left hemisphere, both word processing and facial recognition occur on the right without any impairment to facial recognition ability.

What's the science?

In the neurotypical human brain, the fusiform face area (FFA), a region within the ventro-occipital temporal cortex (vOTC), responds preferentially to faces. Face processing is right-lateralized, meaning the right hemisphere of the FFA is more active and dominant than the left. Conversely, language and visual word form processing are left-lateralized in a region called the visual word form area (VWFA) within the left VOTC. It has been hypothesized that these two lateralization patterns are linked: as children learn to read, the VWFA establishes itself in the left vOTC, either displacing or blocking the expansion of facial processing there, causing face processing to rely more heavily on the right vOTC. While correlations between literacy and face lateralization support this idea, evidence of direct competition between word and face processing remains mixed. This week in the Journal of Neuroscience, Seydell-Greenwald and colleagues used functional MRI (fMRI) to test whether face processing is altered in individuals who suffered a left-hemisphere perinatal stroke (LHPS) and consequently developed right-lateralized language and word processing. 

How did they do it?

The authors performed fMRI on 15 individuals with LHPS (mean age 19 years) who had previously established right-hemisphere language dominance and right-lateralized VWFA and compared them to 14 neurotypical individuals (mean age 16 years) with typical left-hemisphere language dominance. Both groups were fluent readers with comparable language comprehension scores. Participants completed a visual localizer task in which they viewed rapid sequences of images from three categories: faces, places, and word forms, allowing the authors to map and compare the lateralization of face and word form processing across groups. Participants then completed the Cambridge Face Memory Test, a standardized assessment of unfamiliar face recognition, requiring them to learn six faces and then identify them across different viewing angles and conditions. Together, these two tasks allowed the authors to assess both the neural lateralization of face processing and its behavioral consequences in individuals with LHPS relative to unaffected control participants. 

What did they find?

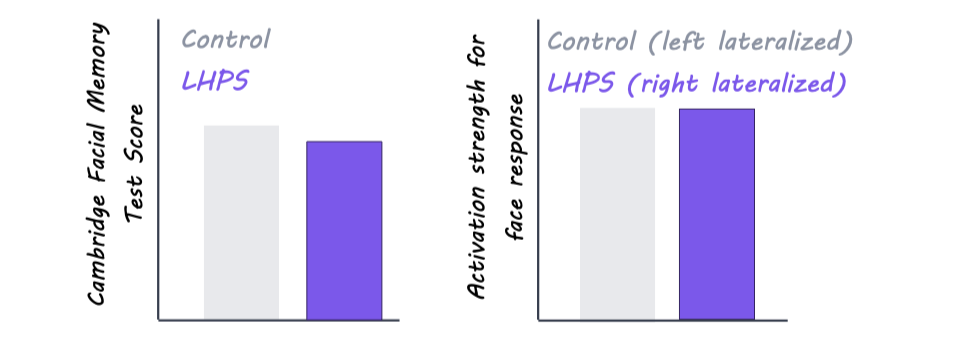
Control participants showed the typical pattern of left-lateralization for word forms and right-lateralization for faces, while the LHPS group was right-lateralized for both. This indicates that when word processing reorganizes to the right hemisphere after an early stroke, face processing does not compensate by shifting to the left. Instead, both functions are supported by the same hemisphere. There were no significant differences in the strength, spatial extent, or peak activation of face responses between the two groups, and both groups showed a positive correlation between face lateralization and word form lateralization, meaning stronger right-lateralization for words was associated with stronger right-lateralization for faces. Lastly, LHPS participants performed slightly but not significantly worse than controls on the Cambridge Face Memory Test, and both groups scored within normal range. Together, these findings suggest that sharing the right vOTC with word form processing does not meaningfully compromise the neural representation of faces or the ability to recognize them. 

What's the impact?

This study was the first to show that although the neurotypical brain delineates facial processing and visual word processing to either the right or left hemisphere, respectively, patients who have experienced early stroke to the left hemisphere can process both faces and written words together in the right hemisphere without any meaningful cost to either. This challenges the long-standing idea that the typical opposite-hemisphere arrangement of face and word processing is driven by competition. These findings provide insight into the key drivers of lateralizing specific neuronal pathways and demonstrate the remarkable capacity of the developing brain to reorganize after injury. 

Access the original scientific publication here.